
Introducing Dr. Bootstaylor

10407677_900069953387799_7072719914479444608_n
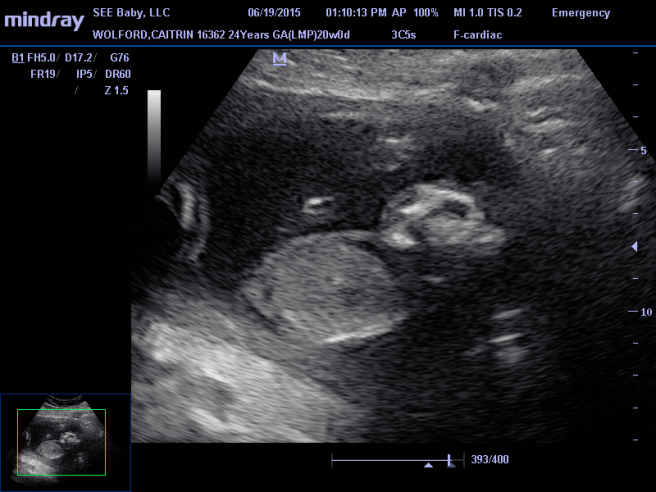
Our sweet Brielle in one of her scans.

We had a wonderful appointment with Dr. Bootstaylor today at Emory University! David and I were a nervous wreck all day, we had no idea how receptive Dr. B would be to how we felt about our baby and what we know she is capable of.

Even though he was incredibly busy today, he made time for us, greeted us (and remembered us) in the waiting room, and brought us to his office. He never once made us feel rushed or as if our questions weren’t important.

We talked about cesarean vs. vaginal delivery, what delivery would be like, hospice, how he felt about her and us, treatment options, etc.

He was very happy we had chosen to keep her and I think excited as well. He told us that he saw this as a real pregnancy and a real baby that deserved just as much care and attention as any other pregnancy. He was not disgusted or annoyed with us keeping a baby that is “incompatible with life” and quite frankly, disagreed with the belief that these babies aren’t important or valuable. He was thrilled with all of the things she can do, and seemed genuinely happy to hear how well she is doing and what a sweet baby she is. We asked him how many babies with anencephaly he had seen go full term (because he has said before that he has seen quite a few babies with anencephaly), he said in 25 years he has seen 10. To be honest, that was more than I was expecting.

We discussed delivery options and he understood our main goal was to see Brielle alive and hold her alive. We talked about how a cesarean would be with him and which incision would be the least traumatizing to my body. The risks are still there, but we agreed a low transverse incision would be best, so I can birth vaginally with my other pregnancies (.2% – 1.5% of uterine rupture). His goals for delivery were exactly what ours were as well. Immediate skin to skin contact, delayed cord clamping (30% of the baby’s blood is the the placenta after delivery so it is best to avoid cutting the cord until the cord stops pulsating), and no restraints during the operation so that I can bond with Brielle. And he made it very clear that she would never have to leave me during the c-section. Vaginal delivery is pretty much however I want to do things, I even get to eat! He told us that it is really too early to decide between the two, and that I may go into spontaneous delivery and take the decision out of our hands, or that I may go full term and then we can schedule a delivery. I appreciated that he wanted to do what was best for us and not what was best for his time or bank account.

He told us that he was open to helping us find treatment and told us that with Brielle we would be the educators to the doctors we come in contact with and he told us we need fortitude, because there is going to be resistance. But he was happy to help and excited to change the way anencephaly is seen. He told us that was our place in life, to bring attention and change to this defect. We agreed around 36 weeks we will see a pediatric neonatologist and discuss treatment options and a plan once she’s born. Which is something David and I will need to be fully educated for. I’ll make an exciting post about this later.

We are so impressed by Dr. Bootstaylor and we adore him. He truly is a Godsend and has been kind and supportive of us through this entire journey. I could not ask for a better or more qualified doctor to help us through this time. Any ATL friends, you need to go to his practice, because he is amazing.


Good Days, Bad Days

24320222040_84dfca5491_o

I have good days and bad days. Today is a bad day. I want to sleep and forget this is all happening, but then I start to panic. I only have so much time with her and I’m terrified of wasting it. And then I think about Christmas and how she’ll just have died. And how can I ever travel again? I can’t leave her alone in a cemetery on Christmas. I know it’s just her earthly body, but it’s all I’ll have left, I have to keep her safe.

And how do I deliver her? Her odds of survival double if I have a c section, but I’ve been told never to have abdominal surgery again. It puts me at risk of death and worsening my gastroparesis. How do I chose between our lives? One mother talked about her son having sores on his exposed head after birth, where skin and brain tissue were rubbed off. How can I let that happen to her? Even though I was told she’d never know pain, she’s been showing signs of pain and sensitivity. How can I do that to her? How do I make that decision? I just want my baby to live. I just want to see her grow up, I’m supposed to go first, not her.

Brielle’s Fetal Behavior

23988888653_3a707d0ec9_o
Image from GoodReads.

When David and I were first told that our baby has anencephaly, we were told that she would never exhibit normal fetal behavior and would not survive. We were told that she was, for all intents and purposes, a vegetable. I was told she would not move like a normal baby in utero and later told all of her movements were merely reflexes. I was also told she would never hear or develop any of her other senses. At barely 20 weeks, I had no idea what to believe. I had felt Brielle move, and it hadn’t felt like a reflex, but then again, I’d just started feeling her move. The week after her diagnosis I attempted to test her ability to understand, I read to her, I smelled flowers, I played her music, and I spoke to her. And here is what I found:

She repeatedly perked up when I said the word Daddy. She had immediate responses to smell, such as flowers, onions, and pineapple (some of her favorite things). She was incredibly quiet and still when I played her some music, her first song she danced to was on Father’s Day to Third Eye Blind’s “How’s It Going To Be.” Later that evening she went crazy dancing to OMI’s “Cheerleader” she especially liked the trumpet part. The more music I played to her, the more I learned that she preferred specific instruments or rhythmic beats. I read her books, and she remained quiet on nearly all of them except for “The Silver Slippers” by Elizabeth Koda-Callan, to which multiple times she would move around and kick me. Since then, we have continued to read to her Bible stories and she has, seemingly, found some more interesting than others. For a week, when David would come home and open the garage door, she would start kicking. She likes to be active for a few hours at a time in the mornings, late afternoon, and late evening, the rest of the day she prefers to sleep…and she’s a heavy sleeper like her Mommy. When I deny her a craving she will kick for hours and will not cease until I indulge that craving. When I wake up from a nap and say something, she jumps with excitement. During our second opinion ultrasound she rubbed her feet together, just like I do as I fall asleep, and just like my Papa did as he fell asleep.

When I asked the second doctor we spoke to about her, this doctor told me all of these things were just reflexes and she laughed at me for thinking that a fetus could respond to a book. And yet there has been plenty of research that shows that a fetus does in fact prefer some stories over others, although they don’t know why.

Based on my time with Brielle, I’ve learned she is not a vegetable, she can hear, she has likes, she’s stubborn, she likes music, and she loves to hear my voice. She even knows when I am speaking directly to her, she kicks in response to some of the things I say, I don’t understand it, but this is what I’m observing. I’ve seen my baby girl’s head twice, and each time it was missing a skull. There is no doubt that she has anencephaly. What I doubt is how well the medical community understands this disability. Am I missing something? Could this all just be a reflex? I find my personal doubts hard to believe as I feel her now moving to one of her favorites by The Killers “All These Things That I’ve Done.” Why do I feel all of these things and how is she so cognizant, if she is lacking a brain? And why can’t anyone save my baby? She is so sweet and gentle, why does the medical community not find her worth saving?

Live Anencephalic Organ Donation

23989205993_b893a0aec8_o

One of the most sickening and infuriating things about carrying a baby with anencephaly is that the medical community views these babies as brain dead and with a lack of “personhood” (the quality or condition of being an individual person). Often times this leads to a push to offer these babies up for organ donation, as if to say they can live on in another’s baby. Here’s the problem with that logic, these babies are individual people with likes and dislikes, they may be missing parts of their brains, but they are still people and any mother who has carried one of these babies will testify to that. If they are born alive, they are often cognizant (although they may lack the ability to communicate), and they are absolutely not brain dead, or vegetative.

To donate the organs of an anencephalic baby (which does happen), a surgeon would have to take a living and aware baby, put it under anesthesia and remove it’s organs piece by piece. This sickens me. A study in 1988 indicates that anencephalic babies are functionally closer to normal newborns than they are to adults in chronic vegetative states. How then is it ok to treat them so brutally? Germany, Japan, and Holland have programs in place for anencephalic organ donation, and many are trying to start programs like that here in the U.S. This cannot happen.

